
2027 Bus Driver Benefit Guide
This guide provides a comprehensive overview of the benefits available to bus drivers at Noblesville Schools in 2027.
Enroll in Benefits 2027 Bus Driver Benefit Guide

The health and financial security of you and your family is important to us. Our benefit program provides plans that can enhance the lives of you and your family – both now and in the future. As an eligible employee, you will be asked to make decisions about the employee benefits described in this guide. Take time to read it carefully and use the available resources to ensure you make the decisions that are right for you and your family. Your Employee Benefits 2027 PLAN YEAR

Who is eligible for benefits? Qualifying Events You may make a change to your enrolled benefits if you have a qualified status change, such as: marriage, divorce, birth of a child, adoption, death, changes in spouse’s benefits, and more. Spouse & Legal Dependents Your spouse is eligible for medical, dental, and vision as well as legal dependents up to age 26. Eligible children are defined as natural children, legally adopted children, step-children, and children for whom you have legal guardianship. Your children of any age are also eligible if you support them, and they are incapable of self-support due to disability. Dependents turning 26 are eligible to stay on the plan until December 31st of the year they turn 26. Full-Time Employees All full-time Noblesville Schools employees working at are eligible to enroll in our benefit plan program. You may insure yourself and eligible family members under the program.
Who pays for benefits? Coverage Carrier Noblesville Schools Pays Employee Pays Medical UHC / Surest Dental Delta Dental Vision EyeMed Basic Life + AD&D Voya Voluntary Life + AD&D Voya Short-Term Disability Voya Long-Term Disability Voya Accident Insurance Voya Critical Illness Insurance Voya Hospital Indemnity Voya
Medical plan costs Surest Plan Core HDHP Basic HDHP 24 Deductions: $263.90 Employee 20 Deductions: $316.68 24 Deductions: $202.51 20 Deductions: $243.01 24 Deductions: $77.82 20 Deductions: $93.38 24 Deductions: $658.48 + Spouse 20 Deductions: $790.18 24 Deductions: $500.21 20 Deductions: $600.25 24 Deductions: $391.35 20 Deductions: $469.61 24 Deductions: $503.38 + Child(ren) 20 Deductions: $604.06 24 Deductions: $383.26 20 Deductions: $459.91 24 Deductions: $298.41 20 Deductions: $358.09 24 Deductions: $722.54 Family 20 Deductions: $867.04 24 Deductions: $548.53 20 Deductions: $658.23 24 Deductions: $429.80 20 Deductions: $515.76
Dental & vision plan costs Dental Plan Vision Plan 24 Deductions: $3.67 24 Deductions: $0.58 Employee | 20 Deductions: $4.40 | 20 Deductions: $0.70 | | 24 Deductions: | $7.34 | 24 Deductions: | $1.16 | | + Spouse | | 20 Deductions: | $8.80 | 20 Deductions: $1.39 | | 24 Deductions: | $9.78 | 24 Deductions: | $1.17 | | + Child(ren) | | 20 Deductions: | $11.73 | 20 Deductions: $1.40 | 24 Deductions: $14.61 24 Deductions: $1.86 Family 20 Deductions: $17.53 20 Deductions: $2.23
For 2027, Noblesville is offering a choice between two HDHP plans available through UnitedHealthcare, and a copay-only plan available through Surest. Medical Coverage UHC & SUREST UHC Member Portal Surest Member Portal
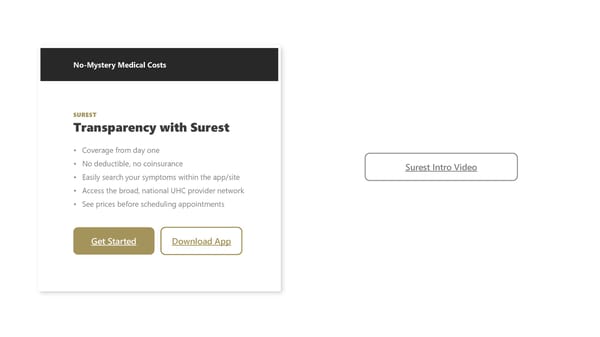
No-Mystery Medical Costs Surest Intro Video • Coverage from day one • No deductible, no coinsurance • Easily search your symptoms within the app/site • Access the broad, national UHC provider network • See prices before scheduling appointments Transparency with Surest SUREST Get Started Download App
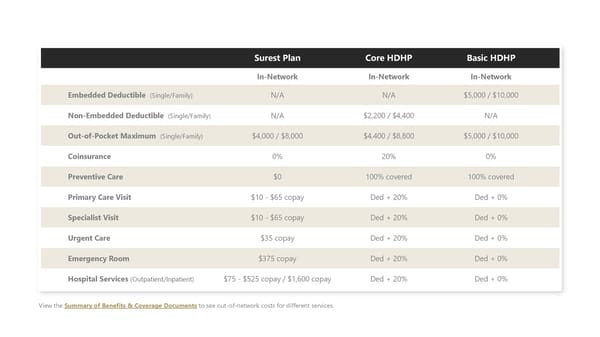
Surest Plan Core HDHP Basic HDHP | In-Network | In-Network | In-Network | | Embedded Deductible (Single/Family) | N/A | N/A | $5,000 / $10,000 | | Non-Embedded Deductible (Single/Family) | N/A | $2,200 / $4,400 | N/A | | Out-of-Pocket Maximum (Single/Family) | $4,000 / $8,000 | $4,400 / $8,800 | $5,000 / $10,000 | | Coinsurance | 0% | 20% | 0% | | Preventive Care | $0 | 100% covered | 100% covered | | Primary Care Visit | $10 - $65 copay | Ded + 20% | Ded + 0% | | Specialist Visit | $10 - $65 copay | Ded + 20% | Ded + 0% | | Urgent Care | $35 copay | Ded + 20% | Ded + 0% | | Emergency Room | $375 copay | Ded + 20% | Ded + 0% | Hospital Services (Outpatient/Inpatient) $75 - $525 copay / $1,600 copay Ded + 20% Ded + 0% View the Summary of Benefits & Coverage Documents to see out-of-network costs for different services.
For 2027, CVS Caremark will continue to be our dedicated partner for pharmacy management. Caremark’s network includes pharmacies such as Walgreens, CVS, and Walmart. Mail-order prescriptions can be ordered directly through Caremark by using the member portal below. Prescription Benefits CVS CAREMARK Caremark Member Portal
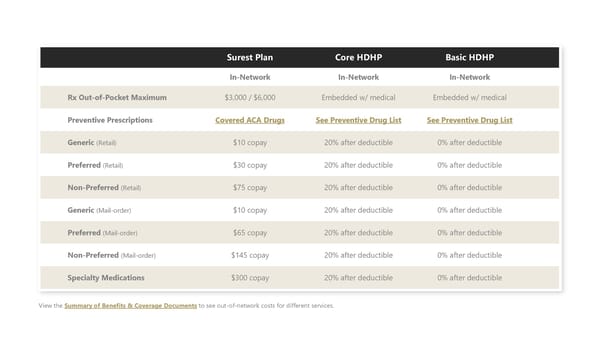
| Surest Plan | Core HDHP | Basic HDHP | | In-Network | In-Network | In-Network | | Rx Out-of-Pocket Maximum | $3,000 / $6,000 | Embedded w/ medical | Embedded w/ medical | | Preventive Prescriptions | Covered ACA Drugs | See Preventive Drug List | See Preventive Drug List | | Generic (Retail) | $10 copay | 20% after deductible | 0% after deductible | | Preferred (Retail) | $30 copay | 20% after deductible | 0% after deductible | | Non-Preferred (Retail) | $75 copay | 20% after deductible | 0% after deductible | | Generic (Mail-order) | $10 copay | 20% after deductible | 0% after deductible | | Preferred (Mail-order) | $65 copay | 20% after deductible | 0% after deductible | | Non-Preferred (Mail-order) | $145 copay | 20% after deductible | 0% after deductible | | Specialty Medications | $300 copay | 20% after deductible | 0% after deductible | View the Summary of Benefits & Coverage Documents to see out-of-network costs for different services.
Rx cost control resources Search your Prescription(s) Free Rx Cost Analysis Rx Help Centers The Rx Help Centers provide members with assistance in finding resources for high-cost, brand-name medications by advocating directly on their behalf with drug manufacturers. CostPlus Drug Company Mark Cuban’s online pharmacy bypasses PBMs by offering generic medications directly to consumers with transparent pricing models: the cost of drug + 15% markup + pharmacy fee. Search your Prescription(s) GoodRx Compare prescription drug prices and find discounts at local pharmacies. You simply search for your medication, choose a pharmacy, and show the GoodRx coupon when you pay.
Find providers, view your ID card, and more online or using the Delta Dental member portal below. Dental Coverage DELTA DENTAL Delta Member Portal
Delta Dental Plan In-Network Out-of-Network Deductible (Single/Family) None $25 / $75 Annual Plan Maximum $1,250/person $1,250/person Preventive Services You pay 0% You pay 0% Basic Services You pay 10% You pay 15% Major Services You pay 40% You pay 45% Orthodontia Services You pay 50% You pay 50% Orthodontia Lifetime Maximum $1,250 $1,000

Download the App Delta Dental’s free mobile app makes it easy for you to make the most of your dental benefits so you can maximize your oral health, wherever you are. Download the Delta Dental App DELTA DENTAL • Check benefits and claims • Find a dentist near you • View mobile ID card • Toothbrush timer APP FEATURES
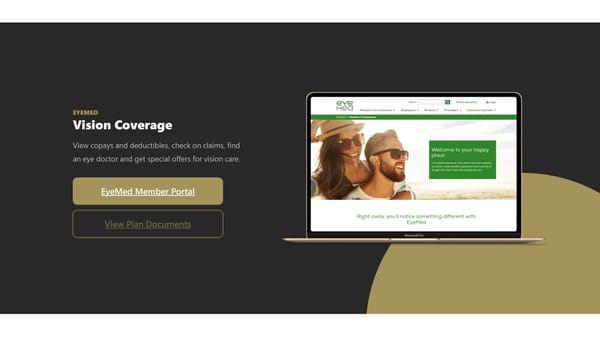
View copays and deductibles, check on claims, find an eye doctor and get special offers for vision care. Vision Coverage EYEMED EyeMed Member Portal
EyeMed Vision Plan In-Network Out-of-Network Benefit Frequency Eye Exam $10 copay Up to $40 reimbursement 1x every year $130 allowance, then Eyeglass Frames 20% of remaining balance Up to $65 reimbursement 1x every year Lenses (Single/Bifocal/Trifocal/Lenticular) $15 copay $30 - $70 reimbursement 1x every year Contact Lenses (Conventional) $130 allowance, then Up to $65 reimbursement 1x every year 15% of remaining balance Contact Lenses (Medically-necessary) 100% covered Up to $300 reimbursement 1x every year
Download the App Get the most from your EyeMed vision benefit. The EyeMed mobile app makes it easy for you to manage your benefits, find vision care, and more. Download the EyeMed App EYEMED • See benefits/eligibility at a glance • Find an in-network eye doctor • View your ID Card • Set upcoming exams • Contact lens replacement reminders • Access interactive vision guides APP FEATURES
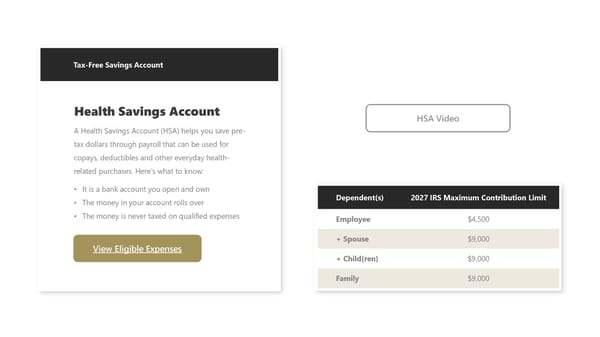
Tax-Free Savings Account Health Savings Account HSA Video A Health Savings Account (HSA) helps you save pre- tax dollars through payroll that can be used for copays, deductibles and other everyday health- related purchases. Here’s what to know: • It is a bank account you open and own | • The money in your account rolls over | Dependent(s) | 2027 IRS Maximum Contribution Limit | | • The money is never taxed on qualified expenses | Employee | $4,500 | | + Spouse | $9,000 | | View Eligible Expenses | | + Child(ren) | $9,000 | | Family | $9,000 |
Paying a bill with your HSA 1 2 3 4 5 You get healthcare Visit a doctor or healthcare provider. After your visit, they send the claim to your health plan. Plan calculates what you owe Your health plan reviews the claim and calculates how much you’re responsible for paying. You receive the explanation Your health plan sends you an explanation of benefits (EOB) showing what was covered and what you owe. You receive the bill Your healthcare provider will then send you a bill for the amount you owe after insurance. Pay with your HSA Use your health savings account funds to pay the bill—or reimburse yourself if you paid out-of-pocket.
Shop HSA Store In addition to paying for prescriptions, copays, and deductibles - you can spend your HSA dollars on a wide range of eligible health-related essentials. Shop Eligible Items on the HSA Store HSA STORE • First-aid and diagnostic supplies • Over-the-counter medicines • Skin and suncare products • Eye and ear care products • Weight loss: eligible GLP-1 medications • Brand names: OURA Ring, Warby Parker, and BetterHelp ELIGIBLE ITEMS Eligible Expense List
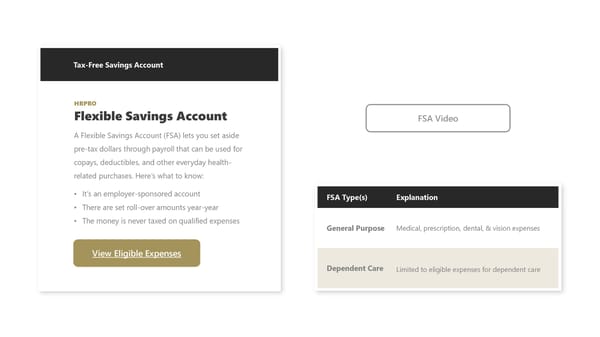
A Flexible Savings Account (FSA) lets you set aside pre-tax dollars through payroll that can be used for copays, deductibles, and other everyday health- related purchases. Here’s what to know: • It’s an employer-sponsored account • There are set roll-over amounts year-year • The money is never taxed on qualified expenses Flexible Savings Account HRPRO FSA Video FSA Type(s) Explanation General Purpose Medical, prescription, dental, & vision expenses Dependent Care Limited to eligible expenses for dependent care Tax-Free Savings Account View Eligible Expenses
Shop FSA Store The FSA Store lets you shop a wide range of health-related, IRS-approved expenses that you can pay for with your Flexible Spending Account. Shop Eligible Items on the FSA Store FSA STORE • First-aid and diagnostic supplies • Over-the-counter medicines • Skin and suncare products • Eye and ear care products • Weight loss: eligible GLP-1 medications • Brand names: OURA Ring, Warby Parker, and BetterHelp ELIGIBLE ITEMS Eligible Expense List
We provide full-time employees with a suite of additional complementary and voluntary benefits. Additional Benefits VOYA Voya Benefits Portal
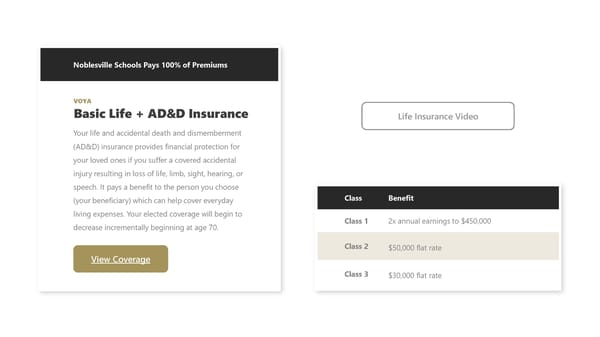
Noblesville Schools Pays 100% of Premiums Life Insurance Video Your life and accidental death and dismemberment (AD&D) insurance provides financial protection for your loved ones if you suffer a covered accidental injury resulting in loss of life, limb, sight, hearing, or speech. It pays a benefit to the person you choose (your beneficiary) which can help cover everyday living expenses. Your elected coverage will begin to decrease incrementally beginning at age 70. Basic Life + AD&D Insurance VOYA View Coverage Class Benefit Class 1 2x annual earnings to $450,000 Class 2 $50,000 flat rate Class 3 $30,000 flat rate
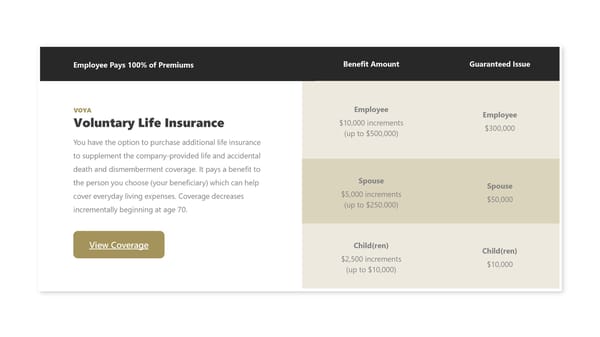
You have the option to purchase additional life insurance to supplement the company-provided life and accidental death and dismemberment coverage. It pays a benefit to the person you choose (your beneficiary) which can help cover everyday living expenses. Coverage decreases incrementally beginning at age 70. Voluntary Life Insurance VOYA View Coverage Benefit Amount Guaranteed Issue Employee $10,000 increments (up to $500,000) Employee $300,000 Spouse $5,000 increments (up to $250,000) Spouse $50,000 Child(ren) $2,500 increments (up to $10,000) Child(ren) $10,000 Employee Pays 100% of Premiums
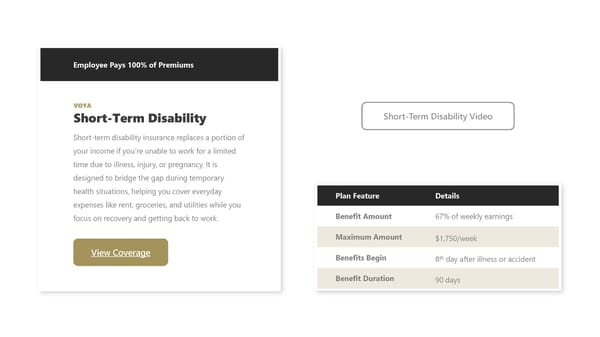
Employee Pays 100% of Premiums Short-Term Disability Video Short-term disability insurance replaces a portion of your income if you’re unable to work for a limited time due to illness, injury, or pregnancy. It is designed to bridge the gap during temporary health situations, helping you cover everyday expenses like rent, groceries, and utilities while you focus on recovery and getting back to work. Short-Term Disability VOYA View Coverage Plan Feature Details Benefit Amount 67% of weekly earnings Maximum Amount $1,750/week Benefits Begin 8th day after illness or accident Benefit Duration 90 days
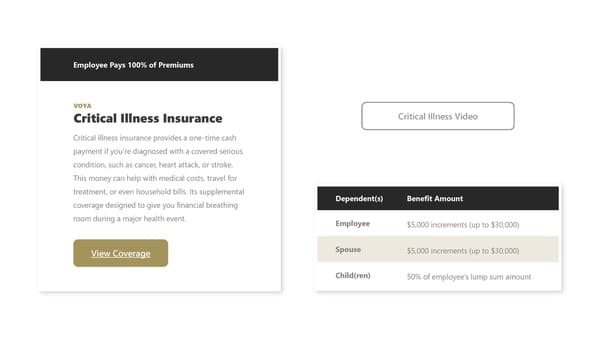
Critical illness insurance provides a one-time cash payment if you’re diagnosed with a covered serious condition, such as cancer, heart attack, or stroke. This money can help with medical costs, travel for treatment, or even household bills. Its supplemental coverage designed to give you financial breathing room during a major health event. Critical Illness Insurance VOYA View Coverage Employee Pays 100% of Premiums Dependent(s) Benefit Amount Employee $5,000 increments (up to $30,000) Spouse $5,000 increments (up to $30,000) Child(ren) 50% of employee’s lump sum amount Critical Illness Video
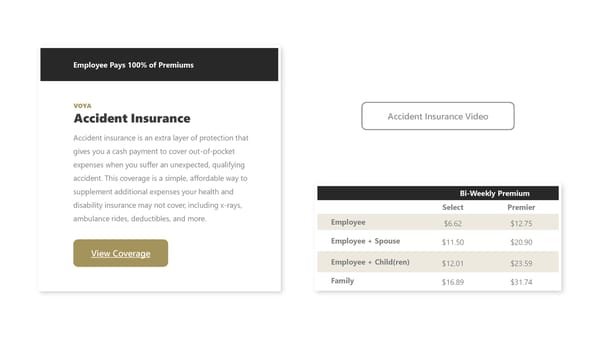
Employee Pays 100% of Premiums VOYA | Accident Insurance | Accident Insurance Video | | Accident insurance is an extra layer of protection that | | gives you a cash payment to cover out-of-pocket | | expenses when you suffer an unexpected, qualifying | | accident. This coverage is a simple, affordable way to | | supplement additional expenses your health and | Bi-Weekly Premium | | disability insurance may not cover, including x-rays, | Select | Premier | | ambulance rides, deductibles, and more. | Employee | $6.62 | $12.75 | | Employee + Spouse | $11.50 | $20.90 | | View Coverage | | Employee + Child(ren) | $12.01 | $23.59 | | Family | $16.89 | $31.74 |
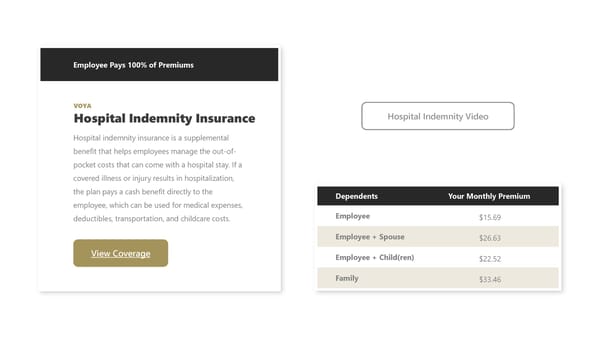
Employee Pays 100% of Premiums VOYA | Hospital Indemnity Insurance | Hospital Indemnity Video | | Hospital indemnity insurance is a supplemental | | benefit that helps employees manage the out-of- | | pocket costs that can come with a hospital stay. If a | | covered illness or injury results in hospitalization, | | the plan pays a cash benefit directly to the | | Dependents | Your Monthly Premium | | employee, which can be used for medical expenses, deductibles, transportation, and childcare costs. | Employee | $15.69 | | Employee + Spouse | $26.63 | | View Coverage | Employee + Child(ren) | $22.52 | | Family | $33.46 |
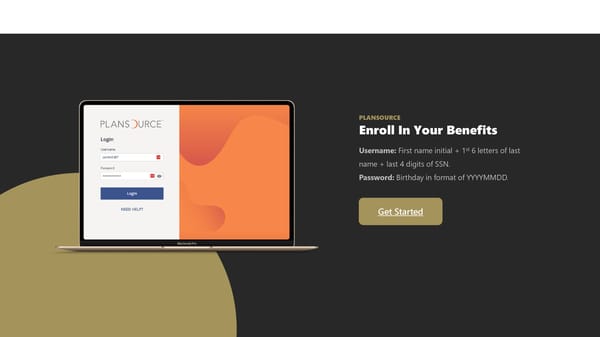
Username: First name initial + 1st 6 letters of last name + last 4 digits of SSN. Password: Birthday in format of YYYYMMDD. Enroll In Your Benefits PLANSOURCE Get Started
| 2027 Pay & Deduction Schedule | Payday | 24 Deductions | 20 Deductions | | January | February | March | April | | 1 | 2 | 31 | 1 | 2 | 3 | 4 | 5 | 6 | 1 | 2 | 3 | 4 | 5 | 6 | 1 | 2 | 3 | | 3 | 4 | 5 | 6 | 7 | 8 | 9 | 7 | 8 | 9 | 10 | 11 | 12 | 13 | 7 | 8 | 9 | 10 | 11 | 12 | 13 | 4 | 5 | 6 | 7 | 8 | 9 | 10 | | 10 | 11 | 12 | 13 | 14 | 15 | 16 | 14 | 15 | 16 | 17 | 18 | 19 | 20 | 14 | 15 | 16 | 17 | 18 | 19 | 20 | 11 | 12 | 13 | 14 | 15 | 16 | 17 | | 17 | 18 | 19 | 20 | 21 | 22 | 23 | 21 | 22 | 23 | 24 | 25 | 26 | 27 | 21 | 22 | 23 | 24 | 25 | 26 | 27 | 18 | 19 | 20 | 21 | 22 | 23 | 24 | | 24 | 25 | 26 | 27 | 28 | 29 | 30 | 28 | 28 | 29 | 30 | 31 | 25 | 26 | 27 | 28 | 29 | 30 | | May | June | July | August | | 1 | 30 | 31 | 1 | 2 | 3 | 4 | 5 | 1 | 2 | 3 | 1 | 2 | 3 | 4 | 5 | 6 | 7 | | 2 | 3 | 4 | 5 | 6 | 7 | 8 | 6 | 7 | 8 | 9 | 10 | 11 | 12 | 4 | 5 | 6 | 7 | 8 | 9 | 10 | 8 | 9 | 10 | 11 | 12 | 13 | 14 | | 9 | 10 | 11 | 12 | 13 | 14 | 15 | 13 | 14 | 15 | 16 | 17 | 18 | 19 | 11 | 12 | 13 | 14 | 15 | 16 | 17 | 15 | 16 | 17 | 18 | 19 | 20 | 21 | | 16 | 17 | 18 | 19 | 20 | 21 | 22 | 20 | 21 | 22 | 23 | 24 | 25 | 26 | 18 | 19 | 20 | 21 | 22 | 23 | 24 | 22 | 23 | 24 | 25 | 26 | 27 | 28 | | 23 | 24 | 25 | 26 | 27 | 28 | 29 | 27 | 28 | 29 | 30 | 25 | 26 | 27 | 28 | 29 | 30 | 31 | 29 | 30 | 31 | | September | October | November | January | | 1 | 2 | 3 | 4 | 1 | 2 | 31 | 1 | 2 | 3 | 4 | 5 | 6 | 1 | 2 | 3 | 4 | | 5 | 6 | 7 | 8 | 9 | 10 | 11 | 3 | 4 | 5 | 6 | 7 | 8 | 9 | 7 | 8 | 9 | 10 | 11 | 12 | 13 | 5 | 6 | 7 | 8 | 9 | 10 | 11 | | 12 | 13 | 14 | 15 | 16 | 17 | 18 | 10 | 11 | 12 | 13 | 14 | 15 | 16 | 14 | 15 | 16 | 17 | 18 | 19 | 20 | 12 | 13 | 14 | 15 | 16 | 17 | 18 | | 19 | 20 | 21 | 22 | 23 | 24 | 25 | 17 | 18 | 19 | 20 | 21 | 22 | 23 | 21 | 22 | 23 | 24 | 25 | 26 | 27 | 19 | 20 | 21 | 22 | 23 | 24 | 25 | | 26 | 27 | 28 | 29 | 30 | 24 | 25 | 26 | 27 | 28 | 29 | 30 | 29 | 30 | 26 | 27 | 28 | 29 | 30 | 31 |