
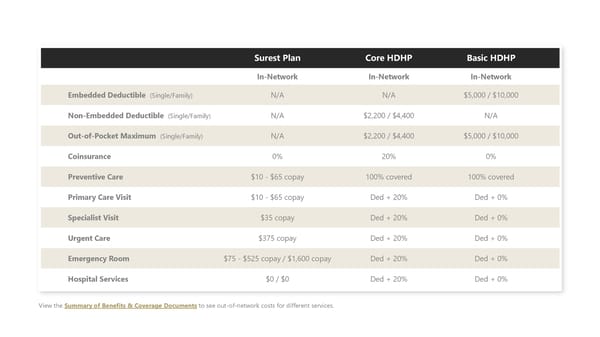
Surest Plan Core HDHP Basic HDHP | In-Network | In-Network | In-Network | | Embedded Deductible (Single/Family) | N/A | N/A | $5,000 / $10,000 | | Non-Embedded Deductible (Single/Family) | N/A | $2,200 / $4,400 | N/A | | Out-of-Pocket Maximum (Single/Family) | N/A | $2,200 / $4,400 | $5,000 / $10,000 | | Coinsurance | 0% | 20% | 0% | | Preventive Care | $10 - $65 copay | 100% covered | 100% covered | | Primary Care Visit | $10 - $65 copay | Ded + 20% | Ded + 0% | | Specialist Visit | $35 copay | Ded + 20% | Ded + 0% | | Urgent Care | $375 copay | Ded + 20% | Ded + 0% | Emergency Room $75 - $525 copay / $1,600 copay Ded + 20% Ded + 0% Hospital Services $0 / $0 Ded + 20% Ded + 0% View the Summary of Benefits & Coverage Documents to see out-of-network costs for different services.
 2027 COBRA Benefit Guide Page 4 Page 6