
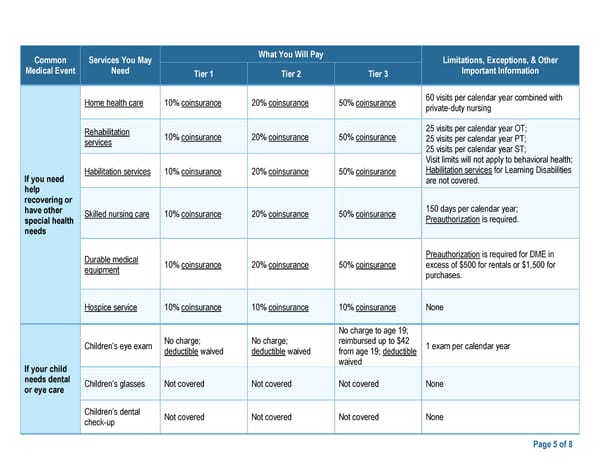
Page 5 of 8 Common Medical Event Services You May Need What You Will Pay Limitations, Exceptions, & Other Tier 1 Tier 2 Tier 3 Important Information If you need help recovering or have other special health needs Home health care 10% coinsurance 20% coinsurance 50% coinsurance 60 visits per calendar year combined with private-duty nursing Rehabilitation services 10% coinsurance 20% coinsurance 50% coinsurance 25 visits per calendar year OT; 25 visits per calendar year PT; 25 visits per calendar year ST; Visit limits will not apply to behavioral health; Habilitation services 10% coinsurance 20% coinsurance 50% coinsurance Habilitation services for Learning Disabilities are not covered. Skilled nursing care 10% coinsurance 20% coinsurance 50% coinsurance 150 days per calendar year; Preauthorization is required. Durable medical 10% coinsurance 20% coinsurance 50% coinsurance equipment Preauthorization is required for DME in excess of $500 for rentals or $1,500 for purchases. Hospice service 10% coinsurance 10% coinsurance 10% coinsurance None If your child needs dental or eye care Children’s eye exam No charge; deductible waived No charge; deductible waived No charge to age 19; reimbursed up to $42 from age 19; deductible waived 1 exam per calendar year Children’s glasses Not covered Not covered Not covered None Children’s dental check-up Not covered Not covered Not covered None
 2027 HSA Plan 1 SBC Page 4 Page 6