
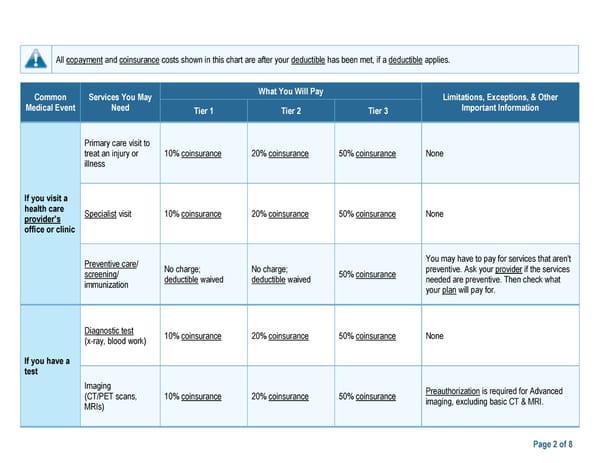
Page 2 of 8 All copayment and coinsurance costs shown in this chart are after your deductible has been met, if a deductible applies. Common Medical Event Services You May Need What You Will Pay Limitations, Exceptions, & Other Tier 1 Tier 2 Tier 3 Important Information If you visit a health care provider’s office or clinic Primary care visit to treat an injury or illness 10% coinsurance 20% coinsurance 50% coinsurance None Specialist visit 10% coinsurance 20% coinsurance 50% coinsurance None Preventive care/ screening/ immunization No charge; deductible waived No charge; 50% coinsurance deductible waived You may have to pay for services that aren't preventive. Ask your provider if the services needed are preventive. Then check what your plan will pay for. If you have a test Diagnostic test 10% coinsurance 20% coinsurance 50% coinsurance None (x-ray, blood work) Imaging (CT/PET scans, MRIs) 10% coinsurance 20% coinsurance 50% coinsurance Preauthorization is required for Advanced imaging, excluding basic CT & MRI.
 2027 HSA Plan 1 SBC Page 1 Page 3