
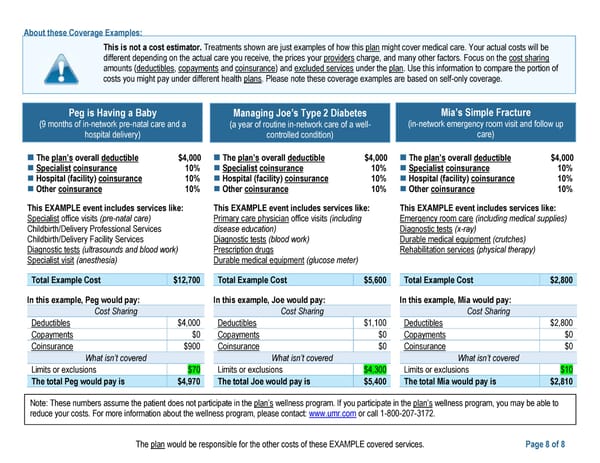
About these Coverage Examples: This is not a cost estimator. Treatments shown are just examples of how this plan might cover medical care. Your actual costs will be different depending on the actual care you receive, the prices your providers charge, and many other factors. Focus on the cost sharing amounts (deductibles, copayments and coinsurance) and excluded services under the plan. Use this information to compare the portion of costs you might pay under different health plans. Please note these coverage examples are based on self-only coverage. | Peg is Having a Baby | Managing Joe’s Type 2 Diabetes | Mia’s Simple Fracture | | (9 months of in-network pre-natal care and a | (a year of routine in-network care of a well- | (in-network emergency room visit and follow up | | hospital delivery) | controlled condition) | care) | | The plan’s overall deductible | $4,000 | The plan’s overall deductible | $4,000 | The plan’s overall deductible | $4,000 | | Specialist coinsurance | 10% | Specialist coinsurance | 10% | Specialist coinsurance | 10% | | Hospital (facility) coinsurance | 10% | Hospital (facility) coinsurance | 10% | Hospital (facility) coinsurance | 10% | | Other coinsurance | 10% | Other coinsurance | 10% | Other coinsurance | 10% | This EXAMPLE event includes services like: This EXAMPLE event includes services like: This EXAMPLE event includes services like: Specialist office visits (pre-natal care) Primary care physician office visits (including Emergency room care (including medical supplies) Childbirth/Delivery Professional Services disease education) Diagnostic tests (x-ray) Childbirth/Delivery Facility Services Diagnostic tests (blood work) Durable medical equipment (crutches) Diagnostic tests (ultrasounds and blood work) Prescription drugs Rehabilitation services (physical therapy) Specialist visit (anesthesia) Durable medical equipment (glucose meter) Total Example Cost $12,700 Total Example Cost $5,600 Total Example Cost $2,800 | In this example, Peg would pay: | In this example, Joe would pay: | In this example, Mia would pay: | | Cost Sharing | Cost Sharing | Cost Sharing | | Deductibles | $4,000 | Deductibles | $1,100 | Deductibles | $2,800 | | Copayments | $0 | Copayments | $0 | Copayments | $0 | | Coinsurance | $900 | Coinsurance | $0 | Coinsurance | $0 | | What isn’t covered | What isn’t covered | What isn’t covered | | Limits or exclusions | $70 | Limits or exclusions | $4,300 | Limits or exclusions | $10 | | The total Peg would pay is | $4,970 | The total Joe would pay is | $5,400 | The total Mia would pay is | $2,810 | Note: These numbers assume the patient does not participate in the plan’s wellness program. If you participate in the plan’s wellness program, you may be able to reduce your costs. For more information about the wellness program, please contact: www.umr.com or call 1-800-207-3172. The plan would be responsible for the other costs of these EXAMPLE covered services. Page 8 of 8
 2027 HSA Plan 2 SBC Page 7