
2027 HSA Plan 2 SBC
This document outlines the health plan coverage, including deductibles and out-of-pocket limits, provided by MT. Vernon Community School Corp for the 2027 coverage period.
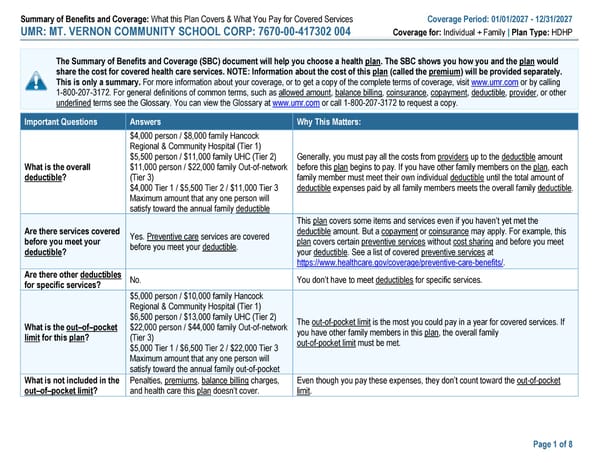
Summary of Benefits and Coverage: What this Plan Covers & What You Pay for Covered Services Coverage Period: 01/01/2027 - 12/31/2027 UMR: MT. VERNON COMMUNITY SCHOOL CORP: 7670-00-417302 004 Coverage for: Individual + Family / Plan Type: HDHP Page 1 of 8 The Summary of Benefits and Coverage (SBC) document will help you choose a health plan. The SBC shows you how you and the plan would share the cost for covered health care services. NOTE: Information about the cost of this plan (called the premium) will be provided separately. This is only a summary. For more information about your coverage, or to get a copy of the complete terms of coverage, visit www.umr.com or by calling 1-800-207-3172. For general definitions of common terms, such as allowed amount, balance billing, coinsurance, copayment, deductible, provider, or other underlined terms see the Glossary. You can view the Glossary at www.umr.com or call 1-800-207-3172 to request a copy. Important Questions Answers Why This Matters: What is the overall deductible? $4,000 person / $8,000 family Hancock Regional & Community Hospital (Tier 1) $5,500 person / $11,000 family UHC (Tier 2) $11,000 person / $22,000 family Out-of-network (Tier 3) $4,000 Tier 1 / $5,500 Tier 2 / $11,000 Tier 3 Maximum amount that any one person will satisfy toward the annual family deductible Generally, you must pay all the costs from providers up to the deductible amount before this plan begins to pay. If you have other family members on the plan, each family member must meet their own individual deductible until the total amount of deductible expenses paid by all family members meets the overall family deductible. Are there services covered before you meet your deductible? Yes. Preventive care services are covered before you meet your deductible. This plan covers some items and services even if you haven’t yet met the deductible amount. But a copayment or coinsurance may apply. For example, this plan covers certain preventive services without cost sharing and before you meet your deductible. See a list of covered preventive services at https://www.healthcare.gov/coverage/preventive-care-benefits/. Are there other deductibles No. You don’t have to meet deductibles for specific services. for specific services? What is the out–of–pocket limit for this plan? $5,000 person / $10,000 family Hancock Regional & Community Hospital (Tier 1) $6,500 person / $13,000 family UHC (Tier 2) $22,000 person / $44,000 family Out-of-network (Tier 3) $5,000 Tier 1 / $6,500 Tier 2 / $22,000 Tier 3 Maximum amount that any one person will satisfy toward the annual family out-of-pocket The out-of-pocket limit is the most you could pay in a year for covered services. If you have other family members in this plan, the overall family out-of-pocket limit must be met. What is not included in the out–of–pocket limit? Penalties, premiums, balance billing charges, and health care this plan doesn’t cover. Even though you pay these expenses, they don’t count toward the out-of-pocket limit.
 2027 HSA Plan 2 SBC Page 2