
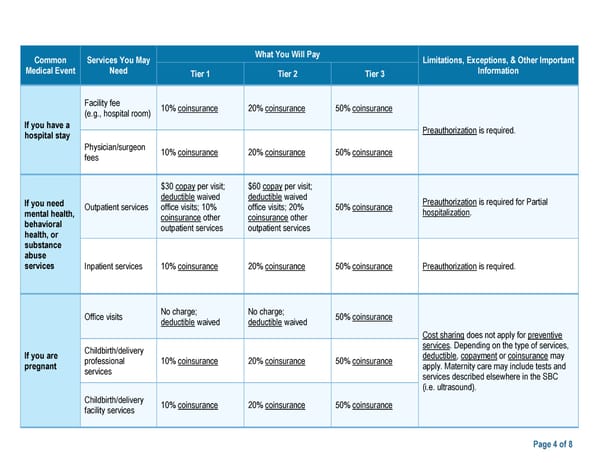
Page 4 of 8 Common Medical Event Services You May Need What You Will Pay Limitations, Exceptions, & Other Important Tier 1 Tier 2 Tier 3 Information If you have a hospital stay Facility fee 10% coinsurance 20% coinsurance 50% coinsurance (e.g., hospital room) Preauthorization is required. Physician/surgeon 10% coinsurance 20% coinsurance 50% coinsurance fees If you need mental health, behavioral health, or substance abuse services Outpatient services $30 copay per visit; deductible waived office visits; 10% coinsurance other outpatient services $60 copay per visit; deductible waived office visits; 20% coinsurance other outpatient services 50% coinsurance Preauthorization is required for Partial hospitalization. Inpatient services 10% coinsurance 20% coinsurance 50% coinsurance Preauthorization is required. If you are pregnant Office visits No charge; deductible waived No charge; 50% coinsurance deductible waived Cost sharing does not apply for preventive services. Depending on the type of services, deductible, copayment or coinsurance may apply. Maternity care may include tests and services described elsewhere in the SBC (i.e. ultrasound). Childbirth/delivery professional services 10% coinsurance 20% coinsurance 50% coinsurance Childbirth/delivery 10% coinsurance 20% coinsurance 50% coinsurance facility services
 2027 PPO Plan SBC Page 3 Page 5