
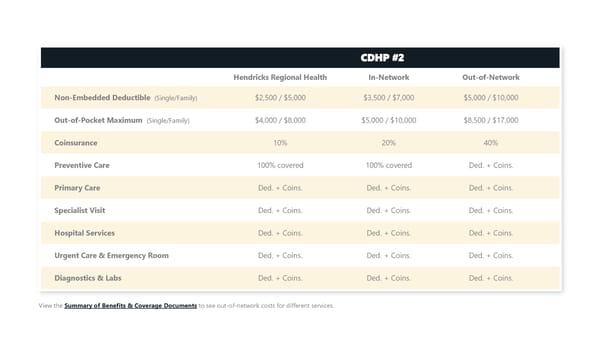
CDHP #2 Hendricks Regional Health In - Network Out - of - Network Non - Embedded Deductible (Single/Family) $2,500 / $5,000 $3,500 / $7,000 $5,000 / $10,000 Out - of - Pocket Maximum (Single/Family) $4,000 / $8,000 $5,000 / $10,000 $8,500 / $17,000 Coinsurance 10% 20% 40% Preventive Care 100% covered 100% covered Ded. + Coins. Primary Care Ded. + Coins. Ded. + Coins. Ded. + Coins. Specialist Visit Ded. + Coins. Ded. + Coins. Ded. + Coins. Hospital Services Ded. + Coins. Ded. + Coins. Ded. + Coins. Urgent Care & Emergency Room Ded. + Coins. Ded. + Coins. Ded. + Coins. Diagnostics & Labs Ded. + Coins. Ded. + Coins. Ded. + Coins. View the Summary of Benefits & Coverage D ocuments to see out - of - network costs for different services.
 2027 Pre-65 Retiree Benefit Guide Page 5 Page 7