
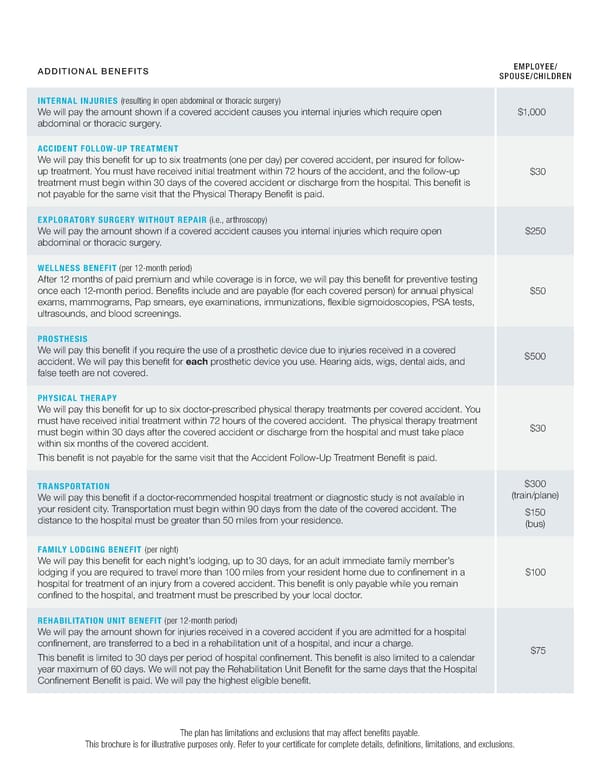
ADDITIONAL BENEFITS EMPLOYEE/ SPOUSE/CHILDREN INTERNAL INJURIES (resulting in open abdominal or thoracic surgery) We will pay the amount shown if a covered accident causes you internal injuries which require open $1,000 abdominal or thoracic surgery. ACCIDENT FOLLOW-UP TREATMENT We will pay this bene昀椀t for up to six treatments (one per day) per covered accident, per insured for follow- up treatment. You must have received initial treatment within 72 hours of the accident, and the follow-up $30 treatment must begin within 30 days of the covered accident or discharge from the hospital. This bene昀椀t is not payable for the same visit that the Physical Therapy Bene昀椀t is paid. EXPLORATORY SURGERY WITHOUT REPAIR (i.e., arthroscopy) We will pay the amount shown if a covered accident causes you internal injuries which require open $250 abdominal or thoracic surgery. WELLNESS BENEFIT (per 12-month period) After 12 months of paid premium and while coverage is in force, we will pay this bene昀椀t for preventive testing once each 12-month period. Bene昀椀ts include and are payable (for each covered person) for annual physical $50 exams, mammograms, Pap smears, eye examinations, immunizations, 昀氀exible sigmoidoscopies, PSA tests, ultrasounds, and blood screenings. PROSTHESIS We will pay this bene昀椀t if you require the use of a prosthetic device due to injuries received in a covered $500 accident. We will pay this bene昀椀t for each prosthetic device you use. Hearing aids, wigs, dental aids, and false teeth are not covered. PHYSICAL THERAPY We will pay this bene昀椀t for up to six doctor-prescribed physical therapy treatments per covered accident. You must have received initial treatment within 72 hours of the covered accident. The physical therapy treatment $30 must begin within 30 days after the covered accident or discharge from the hospital and must take place within six months of the covered accident. This bene昀椀t is not payable for the same visit that the Accident Follow-Up Treatment Bene昀椀t is paid. TRANSPORTATION $300 We will pay this bene昀椀t if a doctor-recommended hospital treatment or diagnostic study is not available in (train/plane) your resident city. Transportation must begin within 90 days from the date of the covered accident. The $150 distance to the hospital must be greater than 50 miles from your residence. (bus) FAMILY LODGING BENEFIT (per night) We will pay this bene昀椀t for each night’s lodging, up to 30 days, for an adult immediate family member’s lodging if you are required to travel more than 100 miles from your resident home due to con昀椀nement in a $100 hospital for treatment of an injury from a covered accident. This bene昀椀t is only payable while you remain con昀椀ned to the hospital, and treatment must be prescribed by your local doctor. REHABILITATION UNIT BENEFIT (per 12-month period) We will pay the amount shown for injuries received in a covered accident if you are admitted for a hospital con昀椀nement, are transferred to a bed in a rehabilitation unit of a hospital, and incur a charge. $75 This bene昀椀t is limited to 30 days per period of hospital con昀椀nement. This bene昀椀t is also limited to a calendar year maximum of 60 days. We will not pay the Rehabilitation Unit Bene昀椀t for the same days that the Hospital Con昀椀nement Bene昀椀t is paid. We will pay the highest eligible bene昀椀t. The plan has limitations and exclusions that may affect benefits payable. The plan has limitations and exclusions that may affect benefits payable. This brochure is for illustrative purposes only. Refer to your certificate for complete details, definitions, limitations, and exclusions.This brochure is for illustrative purposes only. Refer to your certificate for complete details, definitions, limitations, and exclusions.
 Accident Insurance Page 8 Page 10