
[Form] File a Accident/Hospital Claim
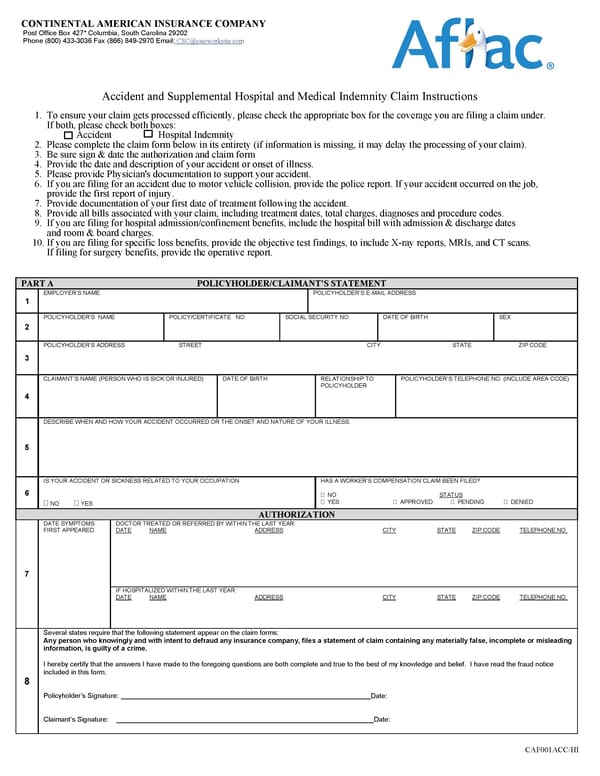
CONTINENTAL AMERICAN INSURANCE COMPANY . Post Office Box 427* Columbia, South Carolina 29202 Phone (800) 433-3036 Fax (866) 849-2970 Email: CSC@caicworksite.com CAF001ACC/HI Accident and Supplemental Hospital and Medical Indemnity Claim Instructions 1. Please complete sections 1 through 7. 2. Read and sign the Authorization, section 8. The authorization will be used in obtaining information needed to process your claim. Failure to complete the Authorization will result in a delay in processing. 3. If your loss is the result of an Accident, please provide a complete description of your accident. If the accident was a motor vehicle accident attach a copy of the police or accident report. If you were injured in an on-job or occupational injury, attach a copy of the first report of injury filed with your employer. 4. If you were first treated at an emergency room, please attach a copy of the discharge papers from the hospital in order for us to verify the first date of treatment. 5. Please attach a copy of all bills and supporting documents related to the treatment of your loss. The medical bills and supporting documents should include the diagnosis, the specific procedure or treatment the covered insured received, the date of service, and the amount charged for physician services, emergency room treatment and supplies. If you are filing for hospital confinement benefits, attach a copy of the itemized hospital bill showing the number of days of hospitalization or an admission and discharge summary. If you are filing during the first year of your coverage effective date and subject to a pre-existing investigation, complete the enclosed pre-existing statement form in full and return to our office with your claim form. PART A POLICYHOLDER/CLAIMANT’S STATEMENT 1 EMPLOYER’S NAME POLICYHOLDER’S E-MAIL ADDRESS 2 POLICYHOLDER’S NAME POLICY/CERTIFICATE NO. SOCIAL SECURITY NO. DATE OF BIRTH SEX 3 POLICYHOLDER’S ADDRESS STREET CITY STATE ZIP CODE 4 CLAIMANT’S NAME (PERSON WHO IS SICK OR INJURED) DATE OF BIRTH RELATIONSHIP TO POLICYHOLDER POLICYHOLDER’S TELEPHONE NO. (INCLUDE AREA CODE) 5 DESCRIBE WHEN AND HOW YOUR ACCIDENT OCCURRED OR THE ONSET AND NATURE OF YOUR ILLNESS. 6 IS YOUR ACCIDENT OR SICKNESS RELATED TO YOUR OCCUPATION � NO � YES HAS A WORKER’S COMPENSATION CLAIM BEEN FILED? � NO STATUS � YES � APPROVED � PENDING � DENIED AUTHORIZATION DOCTOR TREATED OR REFERRED BY WITHIN THE LAST YEAR: DATE NAME ADDRESS CITY STATE ZIP CODE TELEPHONE NO. 7 DATE SYMPTOMS FIRST APPEARED IF HOSPITALIZED WITHIN THE LAST YEAR: DATE NAME ADDRESS CITY STATE ZIP CODE TELEPHONE NO. 8 Several states require that the following statement appear on the claim forms: Any person who knowingly and with intent to defraud any insurance company, files a statement of claim containing any materially false, incomplete or misleading information, is guilty of a crime. I hereby certify that the answers I have made to the foregoing questions are both complete and true to the best of my knowledge and belief. I have read the fraud notice included in this form. Policyholder’s Signature: Date: Claimant’s Signature: Date: 1. To ensure your claim gets processed efficiently, please check the appropriate box for the coverage you are filing a claim under. If both, please check both boxes: Accident Hospital Indemnity 2. Please complete the claim form below in its entirety (if information is missing, it may delay the processing of your claim). 3. Be sure sign & date the authorization and claim form 4. Provide the date and description of your accident or onset of illness. 5. Please provide Physician's documentation to support your accident. 6. If you are filing for an accident due to motor vehicle collision, provide the police report. If your accident occurred on the job, provide the first report of injury. 7. Provide documentation of your first date of treatment following the accident. 8. Provide all bills associated with your claim, including treatment dates, total charges, diagnoses and procedure codes. 9. If you are filing for hospital admission/confinement benefits, include the hospital bill with admission & discharge dates and room & board charges. 10. If you are filing for specific loss benefits, provide the objective test findings, to include X-ray reports, MRIs, and CT scans. If filing for surgery benefits, provide the operative report. Accident and Supplemental Hospital and Medical Indemnity Claim Instructions
 [Form] File a Accident/Hospital Claim Page 2