
PPO Plan - Summary of Benefits & Coverage
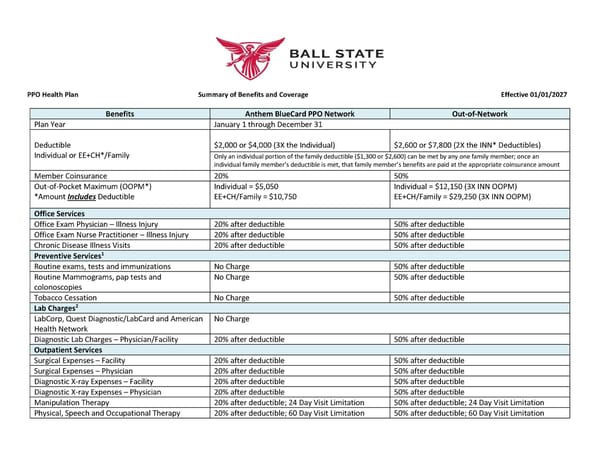
This document provides an overview of the PPO Health Plan, detailing the benefits, deductibles, and coverage options available under the Anthem BlueCard PPO Network and Out-of-Network policies effective from January 1, 2027.
PPO Health Plan Summary of Benefits and Coverage Effective 01/01/2027 Benefits Anthem BlueCard PPO Network Out-of-Network Plan Year January 1 through December 31 Deductible $2,000 or $4,000 (3X the Individual) $2,600 or $7,800 (2X the INN* Deductibles) | Individual or EE+CH*/Family | Only an individual portion of the family deductible ($1,300 or $2,600) can be met by any one family member; once an | | individual family member’s deductible is met, that family member’s benefits are paid at the appropriate coinsurance amount | | Member Coinsurance | 20% | 50% | | Out-of-Pocket Maximum (OOPM*) | Individual = | $5,050 | Individual = | $12,150 (3X INN OOPM) | | *Amount Includes Deductible | EE+CH/Family = | $10,750 | EE+CH/Family = $29,250 (3X INN OOPM) | Office Services Office Exam Physician – Illness Injury 20% after deductible 50% after deductible Office Exam Nurse Practitioner – Illness Injury 20% after deductible 50% after deductible Chronic Disease Illness Visits 20% after deductible 50% after deductible Preventive Services1 Routine exams, tests and immunizations No Charge 50% after deductible Routine Mammograms, pap tests and No Charge 50% after deductible colonoscopies Tobacco Cessation No Charge 50% after deductible Lab Charges2 LabCorp, Quest Diagnostic/LabCard and American No Charge Health Network Diagnostic Lab Charges – Physician/Facility 20% after deductible 50% after deductible Outpatient Services Surgical Expenses – Facility 20% after deductible 50% after deductible Surgical Expenses – Physician 20% after deductible 50% after deductible Diagnostic X-ray Expenses – Facility 20% after deductible 50% after deductible Diagnostic X-ray Expenses – Physician 20% after deductible 50% after deductible Manipulation Therapy 20% after deductible; 24 Day Visit Limitation 50% after deductible; 24 Day Visit Limitation Physical, Speech and Occupational Therapy 20% after deductible; 60 Day Visit Limitation 50% after deductible; 60 Day Visit Limitation
 PPO Plan - Summary of Benefits & Coverage Page 2