
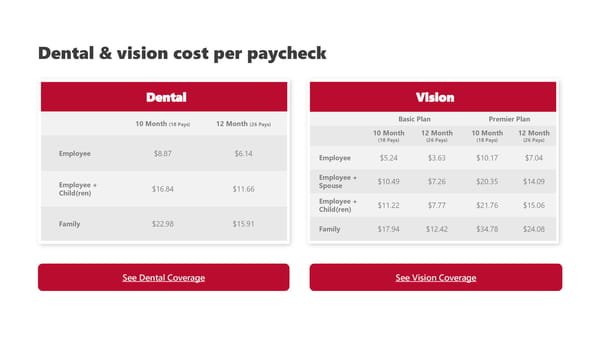
Dental & vision cost per paycheck Dental Vision Basic Plan Premier Plan 10 Month (18 Pays) 12 Month (26 Pays) 10 Month 12 Month 10 Month 12 Month | (18 Pays) | (26 Pays) | (18 Pays) | (26 Pays) | | Employee | $8.87 | $6.14 | Employee | $5.24 | $3.63 | $10.17 | $7.04 | | Employee + | Employee + | $10.49 | $7.26 | $20.35 | $14.09 | | $16.84 | $11.66 | Spouse | | Child(ren) | | Employee + Child(ren) | $11.22 | $7.77 | $21.76 | $15.06 | | Family | $22.98 | $15.91 | | Family | $17.94 | $12.42 | $34.78 | $24.08 | See Dental Coverage See Vision Coverage
 Ball State University 2027 Employee Benefit Guide Page 5 Page 7