
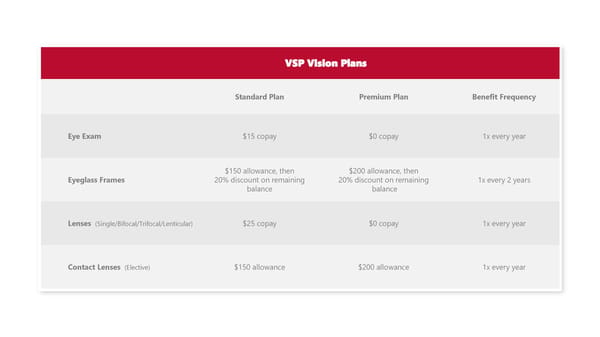
VSP Vision Plans Standard Plan Premium Plan Benefit Frequency Eye Exam $15 copay $0 copay 1x every year Eyeglass Frames $150 allowance, then 20% discount on remaining balance $200 allowance, then 20% discount on remaining balance 1x every 2 years Lenses (Single/Bifocal/Trifocal/Lenticular) $25 copay $0 copay 1x every year Contact Lenses (Elective) $150 allowance $200 allowance 1x every year
 Ball State University 2027 Employee Benefit Guide Page 20 Page 22